What do keloids look like?

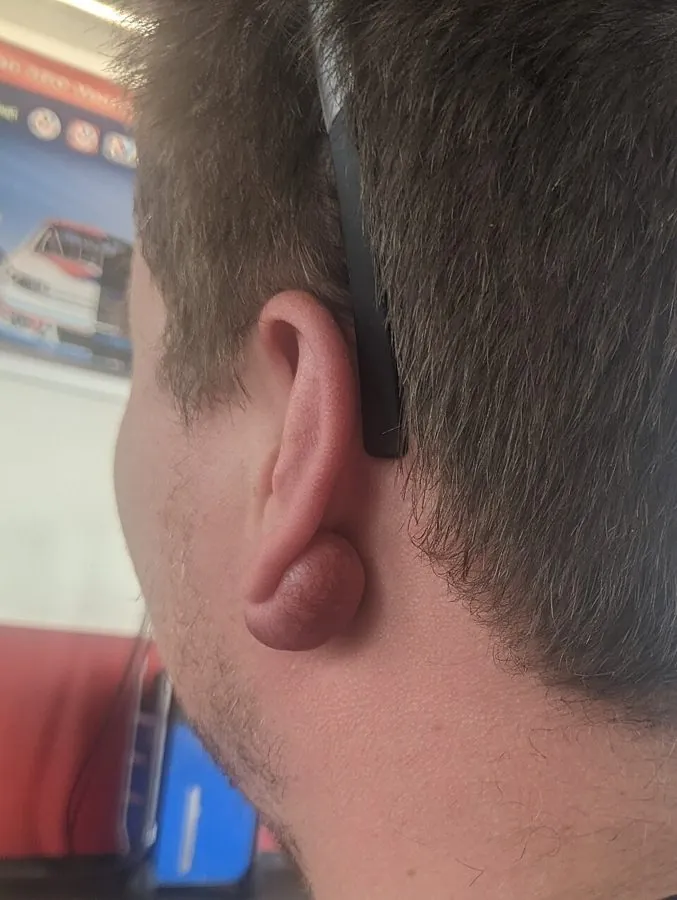
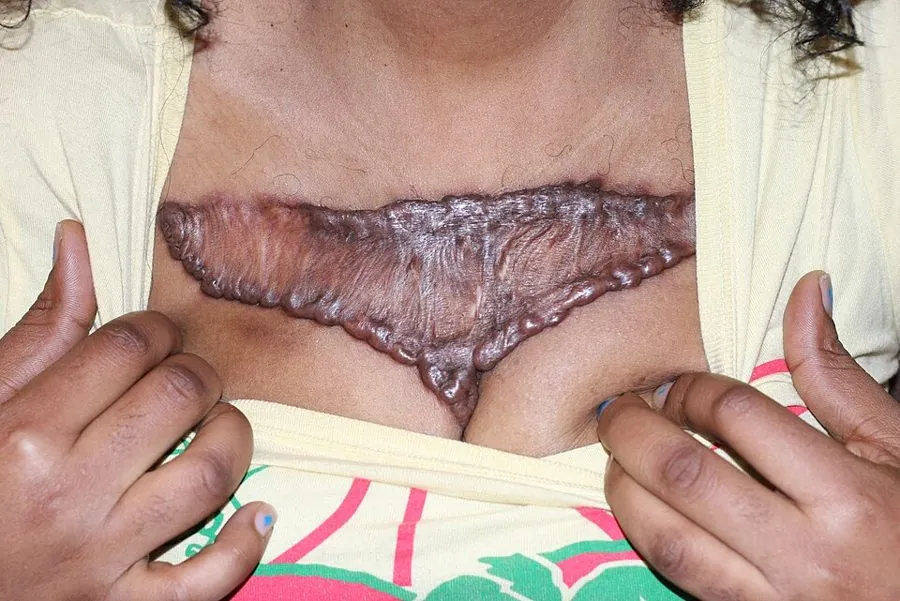
Two overshoots, one spectrum
Both scars are collagen overproduction — fibroblasts that kept building after the repair was done. The international algorithms distinguish them by behaviour: hypertrophic scars rise within the wound, peak, and often regress partially over a year or two; keloids grow beyond the original borders, rarely regress, and can continue expanding for years [1]. Genetics deals the hand — keloid tendency runs in families and is substantially more common in Asian skin — and mechanical tension plays dealer, which is why the chest, shoulders and jawline lead the statistics while the eyelid almost never keloids.
Why is cutting a keloid off the classic mistake?
Excision alone answers a keloid with the one thing keloids love: a fresh wound in keloid-forming skin. The systematic reviews report high recurrence after solo excision — frequently with the new keloid outgrowing the old — which is why every modern algorithm permits surgery only with immediate adjuvant therapy: corticosteroid injection, pressure, silicone, and in selected cases superficial radiotherapy [1,2]. The same logic warns against casual procedures in keloid-prone patients: each piercing and elective excision on high-risk anatomy is a coin flip that should be an informed decision, not an accident.
What actually works for keloids?
A ladder, matched to the scar and climbed with patience [1,2]. Fresh, raised scars: silicone sheeting or gel with pressure — unglamorous, evidence-backed, and the base of every algorithm. Established scars: intralesional corticosteroid injections, the workhorse, softening and flattening over a course of sessions — combined with 5-fluorouracil in resistant disease. Vascular laser calms redness; fractional approaches help texture as adjuncts. Excision is reserved, always chaperoned by immediate adjuvant treatment. Itch and pain — real features of active keloids — respond as the scar quiets. This pathway runs through Dr Sin Yong's keloid treatment programme; raised acne scarring on the jaw and chest is assessed alongside the atrophic scar types, since many faces carry both directions of scarring at once.
What doesn't work for keloids?
Waiting for a keloid to fade — regression is the exception, expansion the pattern. Scar creams and oils on an established keloid — massage-grade intervention for a structural overgrowth. Cutting it off at a general clinic without an adjuvant plan — the recurrence literature is unambiguous. Home remedies — from apple cider vinegar to thread ligation — which add inflammation to tissue that answers inflammation with growth. And piercing the other ear to 'test' — keloid tendency is systemic; the test result is another keloid.
“Cutting a keloid without an adjuvant plan is offering it a fresh wound — the recurrence isn't bad luck, it's the biology you invited.”
— Dr Sin Yong
Dr Sin Yong’s Viewpoint
The keloid patients I meet have usually been offered the one thing keloids love: excision without a plan. Surgery alone answers a keloid with a fresh wound in keloid-forming skin, and the recurrence statistics are unforgiving. My approach is the evidence ladder — injections, patience, staged decisions — and surgery only ever chaperoned by adjuvant treatment.
Prefer Not to Use WhatsApp?
Use the short enquiry form instead →
Leave your name, mobile number and email and the clinic will contact you directly. No obligation.
Prefer a preliminary view first? You can also WhatsApp a photo of the area for Dr Sin Yong to review before you decide on a visit.